

CX NEWS
Four days of Venous content to be run for the first time at Charing Cross
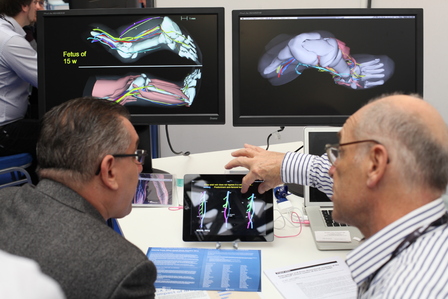
In 2015, the Charing Cross Symposium will dedicate, for the first time, four days of discussion in the venous field addressing both the superficial and deep venous systems. The Symposium is also launching a new CX Venous Workshop, formerly named as CX Office-Based Vein Practice Course, which includes hands-on training on the latest techniques for varicose veins treatment and, for the first time, practical training on deep venous treatment.
On the first day (Tuesday, 28 April) upcoming leading vascular and endovascular experts will present cutting-edge venous investigation at a CX Abstracts‒Venous session. Delegates will also have the chance to visit the CX Venous Workshop, which will run on the following days (Wednesday, 29 April and Thursday, 30 April). On the fourth day, the CX Main Programme will be dedicated to Venous Controversies.
Superficial and deep venous treatment at the core of the Venous Controversies
This year’s Venous Controversies in varicose veins treatment are no longer between surgery and office-based techniques, according to Roger Greenhalgh, (Imperial College, London, UK), chairman of the CX Programme Organising Board. “It seems as if office-based vein techniques have swept the board. Now the controversy seems to be about which method to select in which situation,” he says.
Delegates will learn the latest evidence on varicose veins treatment options with thermal and non-thermal techniques. “We will try to present a balance between data and information that relate to office-based tested techniques that are already established and are probably state-of-the-art alongside techniques that are emerging, and that may not have enough data but nonetheless might represent a completely shift in practice. We are happy for people to find out about these new techniques at Charing Cross first,” says Ian Franklin (London, UK), member of the CX Programme Organising Board.
Commenting on non-thermal techniques, Mark Whiteley (University of Surrey, London, UK), also a member of the CX Programme Organising Board, says: “The newer non-thermal techniques are now joining the endovenous thermal ablative devices and starting to show impressive results. The controversy here will be whether these newer non-thermal methods are now able to replace endothermal ablation in some or all cases.” (See an interview with Whiteley on varicose veins treatment).
Sclerotherapy and laser therapy of cosmetic skin problems will also be discussed.
Deep venous treatment is another major topic of controversy at this year’s CX Symposium. Franklin comments: “Deep venous thrombosis treatment is controversial because it is extremely badly managed in many countries and some people get almost no treatment at all. Nowadays, there are new technologies that help physicians treat deep venous thrombosis effectively. There is a lot to achieve in terms of training and education on how to diagnose deep venous thrombosis promptly with the right method of treatment to guarantee durable results.”
Stephen Black (Guy’s and St Thomas NHS Foundation Trust, London, UK), member of the CX Programme Organising Board, considers that there is a real need to develop the evidence base for treatment options for deep venous thrombosis. At the session on Deep Venous Controversies, delegates will learn about the latest evidence on the current techniques for deep venous thrombosis treatment including new stents and catheter-directed thrombolysis and thrombectomy techniques. (See an interview with Black on deep venous disease treatment).
Imaging for superficial and deep venous treatment is playing a vital role in the diagnosis of these anomalies. Greenhalgh comments: “It appears that imaging is absolutely at the core of intervention in the superficial and deep venous systems. Unfortunately, venous imaging is less than helpful when the patient lies flat and how to image the deep venous system with the patient standing will be discussed.”
The use of current imaging technologies such as duplex, magnetic resonance imaging (MRI) and intravascular ultrasound (IVUS) will be discussed at a session dedicated to this field.
New CX Venous Workshop
The former CX Office-Based Vein Practice Course has changed its name to the CX Venous Workshop because it now encompasses all aspects of venous disease including deep vein thrombosis, intravascular ultrasound and deep vein stenting. The course will continue providing delegates with hands-on training sessions for varicose veins treatment. In 2014, it had a record attendance of over 700 delegates during two days.
The CX Venous Workshop is set out in a very flexible format and will run from 10am until 3pm over two days. There will be different training stations (around 30) led by a physician expert who will be demonstrating a wide range of techniques and procedures in different superficial and deep venous treatment techniques. There is not a rigid timetable and participants can choose their timing at their convenience. The course facilitates one-to-one interaction or discussions in small groups.
Key areas covered include:
- Practical training
- Truncal ablation
- Diagnostic venous ultrasound
- Anatomy
- Venous haemodynamics
- Sclerotherapy
- Thread veins
- Dermal lasers
- Pelvic venous imaging
- Pelvic congestion
- Pelvic veins and haemorrhoids
- IVUS
- Deep vein stenting
- Pelvic vein embolisation
- Lymphoedema
- Endovenous glue
- Mechanochemoablation
- Steam
- Wound care
- Varicose veins
- Perforators
- Tributaries
- Surgery
- Caval filters
- Intermittent pneumatic compression
- Stockings and bandaging
- Neuromuscular electrical stimulation
- Thrombophilia and DVT Venous malformations
The CX Venous Controversies Day will take place at the Charing Cross Symposium on Friday 1 May – Main Auditorium, Olympia Grand, London, UK.
Delegates will have the opportunity to get hands-on training on the latest techniques for superficial and deep venous system treatment at the CX Venous Workshop on Wednesday 29 April and Thursday 30 April – Gallery Upper Level, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to see the CX Venous Workshop
Click here to register
Insights into the current practice for varicose veins treatment

Venous surgeons and phlebologists are spoiled for choice when it comes to office-based technology options for varicose veins. This brings questions such as what technologies are best suited for what patients, what factors should be considered to obtain best results and what is the role of open surgery in the field. Mark Whiteley (University of Surrey, London, UK), member of the CX Programme Organising Board, gives his views on the subject. The latest evidence in this area will be discussed in the Venous Controversies sessions of this year’s CX Main Programme.
Physicians now have a great selection of office-based technologies for the treatment of varicose veins; what method is best for what case?
This has been the major area of my research since starting radiofrequency ablation in March 1999 and it is fair to say that there are many different opinions on this. Most importantly, before this question can even be considered, we need to decide on what constitutes “the best”. In my view, technical perfection is the correct outcome, as this will lead to long-term success and therefore should lead to long-term patient improvement.
However, advocates of techniques with inferior technical results that might require less intervention or fewer injections, point to patient satisfaction as the correct outcome measure to use to assess “the best” treatment method. I believe this is not a good outcome measure to use scientifically. Patient satisfaction can be manipulated by factors other than the treatment itself, particularly by misinformation given to patients in some studies by advocates of one method as to the theoretical risks of other methods that might be used.
In addition, satisfaction has to be measured at one or several points in time—often in the relatively short term. Technical imperfections which are likely to progress to recurrence and reduced patient satisfaction in the long term might be present in the short term. But measuring patient satisfaction alone may miss these out due to the time it takes for the patients to experience the clinical outcomes of the treatment failures.
What factors should be considered to obtain best results in varicose veins treatment?
As with all surgical techniques, there are several factors involved in obtaining the best results. Not only does the technology and device design have to be adequate to the job, but the patient selection needs to provide appropriate cases for the chosen technique and doctors and their teams need to use adequate imaging and procedural technique to get the optimal results.
In addition, patient expectation has to be added, such as whether they are looking for relief of symptoms only or cosmetic perfection and also an acceptable cost for the service.
What office-based technologies are currently showing best results?
Generally, in most hands, endovenous thermoablation shows excellent results for truncal and perforator veins ablation, provided the correct technique is used and an appropriate device for the vein to be treated. Glue and mechanochemical endovenous ablation (MOCA) are starting to show promising results in truncal venous reflux in selected patients whereas foam sclerotherapy is technical disappointing in truncal veins. However, advocates will point to patient satisfaction and re-treatments to argue for its use.
Currently, coil embolisation of refluxing pelvic veins with foam sclerotherapy seems to be the optimal treatment for pelvic venous reflux. Foam sclerotherapy alone or ligation of veins at the pelvic exit points are used by some but need to be proven as effective and acceptable treatments.
For incompetent tributaries and varices, ambulatory phlebectomy is probably optimal for larger veins and foam sclerotherapy for smaller veins— although the new technique of combining both as “foam phlebotomies” is gaining popularity in the USA.
When it comes to neovascular tissue, strip tract revascularisation, feeding veins under patches of telangiectasia and primary avalvular varicose anomalies (PAVA) then foam sclerotherapy is the only effective option.
Finally, for telangiectasia themselves, microsclerotherapy is still the best option as it treats both the visible veins as well as the communicating veins hidden below the surface.
With the outcome of many office-based technologies and their comparable efficacy results with surgery, is there still room for surgery?
No.
Unless one calls ambulatory phlebectomies (surgery), then there is no need to ever perform open surgery for varicose veins anymore. Personally, I have not had to use open surgery for any varicose veins case for over a decade.
At the debate “Duplex scanning is mandatory before treatment of asymptomatic cosmetic thread veins” you will present “For the motion”. Could you tell us the reasons as to why you are supporting this practice?
Since 2001, increasing numbers of research papers have shown that cosmetic thread veins frequently occur in association with underlying venous reflux. In many, if not the majority of cases, this venous reflux leads directly into the thread veins. Furthermore, every case of the complication called telangiectatic matting that I have ever seen after thread vein treatment, has an underlying untreated vein refluxing into the affected patch.
Since instituting a policy of duplex scanning in 2002 in which every patient presenting with cosmetic thread veins of the legs are treated for any underlying venous reflux before proceeding to microsclerotherapy of the thread veins themselves, we have never had a case of telangiectatic matting. Those cases presenting to us with this complication from elsewhere invariably have an underlying vein refluxing into the lesion.
With the explosion of cosmetic clinics starting to offer thread vein treatments, often without duplex ultrasound or even hand held Doppler, it is essential for us as phlebologists and venous surgeons to state that we feel that treatment of thread veins without a duplex ultrasound scan first is a sub-optimal treatment.
The CX Venous Controversies Day will take place at the Charing Cross Symposium on Friday 1 May – Main Auditorium, Olympia Grand, London, UK.
Delegates will have the opportunity to get hands-on training on the latest techniques for varicose veins treatment at the CX Venous Workshop on Wednesday 29 April and Thursday 30 April – Gallery Upper Level, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to see the CX Venous Workshop
Click here to register
Specifically designed stents and imaging: Key players in deep venous treatment

The development of new stents specifically designed for deep venous reconstruction, new techniques for lysis and imaging are playing a key role in the treatment of deep vein thrombosis; an area that, according to Stephen Black (Guy’s and St Thomas NHS Foundation Trust, London, UK), member of the CX Programme Organising Board, has been largely neglected for years. In this interview, Black, who will be chairing a session dedicated to the deep venous system at the Venous Controversies session of CX 2015, speaks about the advances in the field.
What is the major controversy in deep venous treatment?
The main controversy is still the role of the new venous stents and whether these will really change treatment and outcome for patients with chronic obstructive disease causing post thrombotic syndrome.
What methods are showing optimal results in deep venous reconstruction?
Currently the new techniques for lysis and the development of more robust stents have renewed interest in this area. There is certainly great potential with these new developments; however, we still need to be cautious using them given the real absence of descent data to support how, when and why we treat these patients.
Now more stents have been developed specially for the venous anatomy; what impact have these devices had in the treatment of venous disease?
The new stents for venous treatment have raised awareness and led to a renewed focus on what was a largely neglected area for a number of years. Patients with symptoms after deep vein thrombosis are desperate for treatment and have received the answer of nothing to be done for too long. As a group of clinicians we need to embrace this momentum to see if we can make a difference to this group of patients.
What is the role of imaging in deep venous interventions?
The role of imaging is to try and outline anatomy in the best possible manner. In particular, we need to identify what inflow the patient will have into the area that needs stenting and also whether there is a problem more proximally. It helps to identify if there is an obstructive lesion (i.e. May Thurners/Cockets lesion) and whether the patient may require a purely stent procedure or possibly open surgery or a combination of both.
What imaging methods are showing best results?
Intravascular ultrasound (IVUS) and magnetic resonance imaging (MRI) currently have the greatest potential for diagnosis in deep venous treatment. MRI helps to reduce the radiation dose in what are usually a young group of patients. MRI has also the potential to age clot, which is really exciting (delegates will have the opportunity to learn about this MRI capability at the Venous Controversies of the CX Main Programme). IVUS may also help reduce radiation exposure but also provides significantly more real time detail when treating these patients.
Currently we are limited by the imaging modalities all providing us with static images. We need to develop techniques that help identify what the flow is like in the system and measure pressure.
The CX Venous Controversies Day will take place at the Charing Cross Symposium on Friday 1 May – Main Auditorium, Olympia Grand, London, UK.
Delegates will have the opportunity to get hands-on training on the latest techniques for deep venous thrombosis treatment at the CX Venous Workshop on Wednesday 29 April and Thursday 30 April – Gallery Upper Level, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to see the CX Venous Workshop
Click here to register
Best management of short abdominal aortic aneurysm necks to be highlighted in the CX Abdominal Aortic sessions
The controversy around the treatment of infrarenal abdominal aortic aneurysm necks of less than 15mm will spark the discussion in the Abdominal Aortic Controversies Day of this year’s CX Main Programme. Delegates will also hear the latest evidence on the best way to manage a ruptured aneurysm and will have the opportunity to discuss whether too many patients with ruptured abdominal aortic aneurysms are being denied intervention. In addition, the controversy regarding radiation damage to the operator and the patient will be addressed and a series of clinical approaches for elective aneurysm repair will be discussed.
“The management of the aortic neck of less than 15mm is certainly very controversial,” says Roger Greenhalgh (Imperial College, London, UK), chairman of the CX Programme Organising Board. Therefore, he comments, “We will try to address every possible way of treatment.”
Commenting on endovascular aneurysm repair (EVAR) for short necks, Andrew Holden (Auckland City Hospital, Auckland, New Zealand), member of the CX Programme Organising Board, says: “We are aware that using EVAR to treat infrarenal aneurysms with hostile necks has been historically associated with higher aneurysm-related morbidity and mortality. Can new EVAR technologies and techniques change this paradigm?”
Delegates will have the opportunity to hear about the latest evidence regarding EVAR, open surgery and new technologies that are addressing the treatment of infrarenal abdominal aortic neck at the CX Abdominal Aortic Controversies Day (Wednesday 29 April). (Read an interview on the subject with Frans Moll, co-chairman of the CX Programme Organising Board).
Management of ruptured abdominal aortic aneurysms
The latest evidence on the best way to manage a ruptured aneurysm will be presented including the one-year results of the IMPROVE trial and the IPD 3 trial. In the same session, the controversy as to whether many patients with ruptured abdominal aortic aneurysms are denied intervention will be discussed.
Greenhalgh comments: “Perhaps doctors are becoming more concerned about operating for fear of having poor mortality figures. We need to find evidence whether indeed patients are denied intervention.”
Janet Powell (Imperial College, London, UK), member of the CX Programme Organising Board, considers that a few patients are offered repair of ruptured aortic aneurysm because perhaps “not all centres have an endovascular team and facilities available at all times; additionally, there are financial stringencies on healthcare systems and many of these patients may need intervention out of hours.”
Holden adds that many questions on this subject remain unanswered: “Do we have sufficient data to support an ‘EVAR first’ approach for ruptured abdominal aortic aneurysm repair patients? If not, who should be offered EVAR? Does the lower early morbidity associated with EVAR mean more ruptured aneurysms should be treated?”
These and other questions will stir a debate on the subject to be led by Matt Thompson (St George’s Vascular Institute, London, UK) and Peter Lamont (North Briston, NHS Trust, Bristol, UK).
Radiation exposure concerns
Additionally, in the CX Abdominal Aortic Controversies Day, strategies for radiation exposure reduction to the operator and to the patient will be discussed in a mini-symposium. Members of the CX Programme Organising Board consider this subject a top priority in the field. Greenhalgh comments: “The risk of radiation damage to the operator and to the patient is now known to be serious and many physicians have damaged themselves trying to treat their patients.” Powell adds: “Many of the early pioneers of EVAR/TEVAR are now dying of cancer. The importance of reducing radiation burden and safety is one of the key contemporary issues that need to be addressed.”
Subsequently, delegates will learn about a series of clinical approaches for elective aneurysm repair including the latest evidence on a new iliac branch endoprosthesis and treatment strategies for octo- and nonagenarians.
Moreover, the long-term follow-up of EVAR after 20 years of introduction will be also addressed. Holden comments: “The optimum follow-up protocol after EVAR is also likely to be controversial. This is an important discussion as post-procedural surveillance is a major cost contributor to EVAR.”
The CX Abdominal Aortic Day will close with a mini-symposium on the management of type I endoleaks.
The CX Abdominal Aortic Controversies Day will take place at the Charing Cross Symposium on Wednesday 29 April – Main Auditorium, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to register
Frans Moll speaks on the management of short abdominal aortic aneurysm necks

Frans Moll (University Medical Center Utrecht, Utrecht, The Netherlands), co-chairman of the CX Programme Organising Board, gives his views as to why the management of short necks is a hot topic in the field and discusses the current strategies of treatment. He will moderate the session “Procedures for infrarenal abdominal aortic neck” of the CX Abdominal Aortic Controversies Day.
Why is the management of aortic necks of less than 15mm controversial?
There is still an axiom that durability for proximal fixation of the aortic neck with endovascular aneurysm repair (EVAR) depends on sealing and fixation, so you do not only need fixation but you also need a certain amount of sealing zone. The critical sealing zone corresponds to one ring of the stent graft. This is usually between 1.2 and 1.5cm in length.
What are the factors that must be considered when treating short infrarenal aortic necks with endovascular approaches?
If you think that the patient will really benefit from endovascular procedures as opposed to open procedures you need to accept shorter necks (>1.5cm in length). The conditions in which it can be accepted are either suprarenal fixation or T-branched.
What endovascular approaches are currently addressing the management of this type of necks?
In shorter stenting we could use sealing prototypes; for example, there is a device that inflates the sealing zone and another one where the polymer is used to fill the aneurysm sac. You could also use a stent graft that is specifically designed for shorter necks (1.5cm up to 1cm). There is also a system that uses endoluminal staples designed to secure the neck.
At the “Procedures for infrarenal abdominal aortic neck” session, physicians will debate whether EVAR is not sensible for abdominal aortic aneurysms with a neck length shorter than 10mm; are you for or against the motion and why?
I think that necks shorter than 10mm can be treated safely with EVAR but you need to consider the latest generation stent grafts. Not every stent graft is able to provide a good result between 8mm and 10mm length.
The CX Abdominal Aortic Controversies Day will take place at the Charing Cross Symposium on Wednesday 29 April – Main Auditorium, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to register
Management of type B aortic dissection tops agenda in the CX Thoracic Aortic sessions

Type B dissection of the aorta will be the main topic of controversy at this year’s Charing Cross Symposium. Predictions of clinical success after thoracic endovascular aortic repair (TEVAR), factors that predict success after TEVAR for chronic type B dissection, the latest evidence for embolisation of false lumen and spinal cord protection are some of the topics that will be discussed in the CX Thoracic Aortic Controversies Day (Thursday 30 April).
Last year, the majority of delegates who attended a debate titled “For uncomplicated type B dissections, early intervention is indicated” voted against the motion. This year, the debate in this area will assess whether the long-term results following intervention for sub-acute uncomplicated type B dissection warrant intervention.
The Thoracic Aortic Day will also include discussions on the incidence of stroke during aortic arch interventions, treatment options for ascending and arch of the aorta including TEVAR, branched stent grafts for complex arch lesions, open surgery and the use of robotic systems.
Furthermore, amongst the descending thoracic aortic, thoracoabdominal and juxtarenal aortic controversies, the question of threshold diameter for intervention in the thoracic aorta will be raised. Roger Greenhalgh (Imperial College, London, UK), chairman of the CX Programme Organising Board, says: “Evidence for the precise diameter to intervene is extremely sparse and this will be brought out in the session”.
Interview with Andrew Holden, member of the CX Programme Organising Board
Andrew Holden (Auckland City Hospital, Auckland, New Zealand), member of the CX Programme Organising Board and chairman of the session “Controversies in chronic type B dissection of the aorta” speaks on the subject.
Why is the management of chronic type B dissections controversial?
Currently, this is one of the most important sessions at CX and hopefully some consensus will emerge. There is no doubt that treatment of acute complicated type B aortic dissection is widely accepted. What is less clear is whether uncomplicated type B dissection should undergo endovascular treatment and if so when (acute, sub-acute or chronic). In chronic type B dissection, the biggest challenge is to successfully exclude the aneurysmal component (preventing retrograde false lumen perfusion) and maintain branch artery patency.
What are the factors that must be considered when treating chronic type B dissections?
The common thread when treating chronic type B dissection is to exclude the primary (or inflow) intimal tear. It is then unclear how much aorta needs to be covered and how retrograde perfusion of the false lumen can be avoided. In the dissected and aneurysmal abdominal aorta, the challenge is to exclude the false lumen but maintain branch artery patency.
What challenges in TEVAR have to be overcome in order to avoid complications?
Feared complications in TEVAR include retrograde dissection and spinal ischaemia. A number of strategies have been developed and will be discussed at the CX Thoracic Aortic Controversies Day.
The CX Thoracic Aortic Controversies Day will take place at the Charing Cross Symposium on Thursday 30 April – Main Auditorium, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to register