

CX NEWS
New CX Edited Live Cases session focuses on aortic and carotid procedures

With the aim to study key controversies from its Main Programme in technical detail, the Charing Cross Symposium is launching the CX Edited Live Cases, a session that will focus on aortic and carotid procedures. Delegates will have the opportunity to explore the application of different techniques in complex situations, which perhaps could not have been broadcast in a live case because of patient’s safety. Roger Greenhalgh (Imperial College, London, UK), chairman of the CX Programme Organising Board, explains the details of this new session.
Why are the CX Edited Live Cases focusing on the aortic and carotid fields?
The CX Programme Organising Board decided that live cases will be broadcast only in situations where the patient’s life is not at risk and where the surgeon is doing something which is not life-threatening, hence the existence of the CX Live Peripheral Arterial Cases. In peripheral procedures the risk is not as high as in aortic or carotid interventions so we thought it was legitimate to have live cases only for lower limb procedures.
The CX Edited Live Cases are being offered in situations in which the patient’s life or condition could in some way be made worse through having the operator concentrate on filming rather than focusing on the patient. In aortic procedures the slightest slip could be very disastrous for the patient. In this kind of intervention the surgeon requires complete concentration on the patient. Another example is in carotid procedures where there is a risk of embolisation to the brain.
What makes the CX Edited Live Cases different from edited live cases presented at other conferences?
The difference in our Edited Live Cases is that we are relating this session systematically to our Main Programme (Aortic and Carotid) and at all points we will be stressing the evidence that the procedure works. For example, a short presentation in the Main Programme could include a specific device for abdominal aortic aneurysm treatment. In the CX Edited Live Cases that same product can be exposed to show in more detail what is special about it, compared to other aortic devices, and how and why it can be used in that specific case. The topics in the Main Programme normally give the evidence on how to fix a certain condition, but there will always be discussions about why it is thought it works and for the audience to cross question any person. The CX Edited Live Cases will bring an additional space to expand on these discussions and show the technical details.
What kind of procedures should delegates expect to see in the CX Edited Live Cases session?
Delegates should expect to see cases addressing endovascular aneurysm repair (EVAR), thoracic endovascular aortic repair (TEVAR) and endovascular aneurysm sealing (EVAS). The cases will include thoracic complex procedures and abdominal procedures of different types. A carotid mesh procedure, which is aimed to reduce embolisation to the brain to prevent stroke, will also be presented. In addition, we are going to have an Edited Live Case about how to control infection, which you could not do in a live case. We will have approximately 10 Edited Live Cases.
Could you explain what the format of the session will be?
Similar to the Main Programme sessions, the panel of the CX Edited Live Cases will include a chairman, the operator in the Edited Live Case, the phycisian who will be explaining it to the audience and two invited discussants. The speaker will present the case including patient characteristics, reason for the procedure, the necessary investigation undertaken (eg. X-rays), the choice of devices available, the strategies of treatment proposed and all of the pitfalls and concerns raised before the procedure.
After this presentation, a 10-minute edited video will be presented. In order to allow room for discussion about a specific technique the video could be stopped—this is an added benefit you could not have in a live case presentation. This approach will help to improve the educational basis of this session. After that, the aim will be to engage the audience in discussion.
Delegates will also have the opportunity to see these cases post Charing Cross 2015 from a video library that will be created from this initiative.
The CX Edited Live Cases (Aortic and Carotid) will take place at the Charing Cross Symposium on Tuesday 28 April – Grey Learning Centre, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to register
Superficial femoral artery at the centre of the CX Peripheral Arterial sessions

Strategies for treatment of the superficial femoral artery with the concepts of “Leaving nothing behind” or “Leaving something in” will take centre stage in the Peripheral Arterial Controversies session of this year’s CX Main Programme. In addition, delegates will hear about early clinical outcomes with a new flexible endoluminal stent for iliac artery disease. The treatment of popliteal aneurysms by endovascular means will also be subject of discussion, as well as the best treatment options for below-the-knee lesions.
Roger Greenhalgh, chairman of the CX Programme Organising Board, says that the session aiming at “unpacking” the superficial femoral artery will be one of the highlights of the CX Peripheral Arterial Day in the Main Programme (Tuesday 28 April). “We will try to inform the audience about what to do in the superficial femoral artery and when, depending on the type and length of lesion and based on the available evidence.” He adds, “The speakers will consider more severe arterial disease which in their view requires a stent. If something is to be ‘left behind’ this needs to be justified”.
Commenting on the “Leaving nothing behind” concept, Cliff Shearman (University of Southampton, Southampton, UK), member of the CX Organising Board, says: “This is a great idea but the technology (drug-coated balloons, atherectomy) is expensive and we have to see the evidence on how much benefit it does give and for how long.”
Moreover, attendees will learn the results, at five years, of the superficial femoral artery treatment with open surgery.
Delegates will also have the opportunity to discuss in more detail the superficial femoral artery controversies on Thursday 30 April in two roundtables to be held at the CX ilegx Collaboration Day course.
Furthermore, in the CX Peripheral Arterial Day, iliac reconstruction will be addressed with early clinical outcomes of a new flexible endoluminal stent graft. Additionally, the treatment of popliteal aneurysms by endovascular means will be subject of discussion. Commenting on his view on the topic, Shearman says: “Although this is commonly advocated we need to see the long-term results. Also we need to ask ourselves, ‘How many popliteal aneurysms are really suitable for endovascular treatment’?” Physicians will have the chance to discuss their views during this debate at the end of the session.
Below-the-knee treatment options and their effectiveness will also be discussed. Michael Edmonds, member of the CX Organising Board, says: “Addressing below-the-knee intervention strategies is of great importance considering the dramatic rise in the incidence of diabetes mellitus.” Greenhalgh adds: “The below-the-knee arteries are smaller and have difficult technical challenges—the durability of the procedures is seldom stated longer than for two years.”
When treating patients with peripheral arterial disease Greenhalgh says, “advising the patient on self-management including smoking cessation, exercise and healthy living is fundamental”. The second principle, he adds, is to intervene only when it is necessary and avoid making the patient worse. And finally, it is necessary to intervene with a technique as minimal as possible and that can produce durable results. “In the end, it is the patient’s quality of life that matters and if the arterial disease is overcome the symptoms should improve,” he notes.
The CX Peripheral Arterial Day will take place at the Charing Cross Symposium on Tuesday 28 April – Main Auditorium, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to learn more about ilegx
Click here to register
CX ilegx Collaboration Day: Key strategies to save limbs
The CX ilegx Collaboration Day course has been designed to update attendees on the latest treatment strategies developed to avoid the increasing number of unnecessary lower limb amputations—flagship principles of the ilegx initiative. Delegates will learn about the King’s College Hospital open access vascular diabetic foot care pathway—an effective approach which incorporates early diabetic foot referral and interdisciplinary work—which is showing promising results saving limbs.
Delegates will also hear about revascularisation strategies of the ischaemic foot with the latest data in the field; and will have the opportunity to discuss in more detail, in two roundtables led by experts, the controversy of “Leaving something in” or “Leaving nothing behind” in the superficial femoral artery. This subject will be exposed in the CX Main Programme – Peripheral Arterial Controversies (two days before ilegx).
In the commentary below, Michael Edmonds (King’s College Hospital, London, UK), who is one of the founders of ilegx and co-director of the CX ilegx Collaboration Day course, explains the King’s College Hospital pathway. He also writes about the value of endovascular techniques for diabetic foot care and critical limb ischaemia treatment.
This is followed by an interview with Cliff Shearman (University of Southampton, Southampton, UK), co-director of the ilegx Collaboration Day. He talks about what he believes the take-home message from this year’s CX ilegx Collaboration Day will be.
Commentary by Michael Edmonds, ilegx course director
Early referral, fast track care and multidisciplinary work: Key approach to save limbs
The ilegx Collaboration Day will include an account of a modern successful approach to the diabetic ischaemic foot in the King’s College Hospital (London, UK) open access vascular diabetic foot care pathway, which has resulted in greater than 90% limb salvage rate.
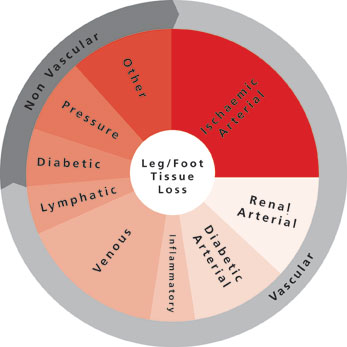
This approach is based on a new understanding of the natural history that has led to a novel classification of the ischaemic diabetic foot, emphasising the importance of the diabetic neuroischaemic foot as well as the critically ischaemic foot. This pathway is operated by an interdisciplinary team comprising surgeon, physician, podiatrist, nurse and orthotist and provides integrated care focused on a diabetic foot clinic. The diabetic foot can deteriorate with alarming speed and for this reason the clinic provides open rapid access to accelerate urgent assessment and to proceed quickly to state-of-the-art interventions in the revascularisation of not only the critically ischaemic foot but also the neuroischaemic foot. This includes prompt decision making within the interdisciplinary team as to proceed to endovascular or open vascular surgery (or both in a hybrid technique), involving revascularisation of both legs and increasingly, pedal arteries. The diabetic neuroischaemic foot is particularly characterised by ulceration and complicating infection and within this interdisciplinary diabetic foot service, modern techniques in wound care and aggressive treatment of infection with surgical debridement and parenteral antibiotics are also important.
The value of endovascular techniques for diabetic foot care and critical limb ischaemia treatment
There is a crucial role for endovascular techniques to revascularise the foot, whether it is to restore blood flow in order to help diabetic ulcers to heal, or longer-term as a treatment for critical limb ischaemia.
It is agreed that the critically ischaemic foot should be urgently revascularised so as to save the limb either by endovascular procedures or open vascular surgery. However, controversy exists when there is a diabetic patient with a neuroischaemic foot ulcer that is not healing in a moderately ischaemic limb. These patients are often not getting the benefit of endovascular procedures in a timely fashion.
Although the neuroischaemic foot would not have got into trouble unless it had been subjected to minor trauma—which is often unsensed because of nerve damage—it is important to understand that, having got into trouble, the ulcer cannot be healed because the blood supply to the foot cannot be increased. Thus there is a crucial role for below-the-knee endovascular procedures to improve the blood supply, even if it is a temporary increase, to get such ulcers healed. Once such ulcers are healed it will not matter if subsequently there is restenosis.
Interview with Cliff Shearman, ilegx course director
In this year’s CX iLegx Collaboration Day, what do you think the take home message will be?
Shearman: Avoiding amputation is relatively easy; it is about early treatment and not ignoring the problem. The biggest barrier to success is poor organisation and lack of awareness of the seriousness of the problem. Solving the problem improves outcomes, improves quality of care and saves a lot of money.
This year’s ilegx roundtables will discuss revascularisation strategies in the superficial femoral artery; do you believe you should “Leave nothing behind” or “Leave something in”?
Shearman: Better understanding of the biology of diabetic vascular disease will lead to better therapies. While it is appealing to consider therapies, which do not leave anything behind, we have to understand what the main effect (short- and medium-term) of an intervention is on the plaque to design the optimum therapy.
About ilegx
The ilegx initiative, launched in 2008, was created in response to the increasing number of lower limb amputations which are mostly due to type II diabetes.
ilegx is a collaboration of like-minded health professionals, patients and care workers who share the view that too many legs are amputated and many of these are completely unnecessary.
The ilegx mission is to attract attention and draw awareness to the need for an improvement in health care in order to lower unnecessary major amputation of legs.
The CX ilegx Collaboration Day will take place at the Charing Cross Symposium on Thursday 30 April – Grey Learning Centre, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to register
CX Live Peripheral Arterial Cases to be broadcast for the first time at the CX Symposium

This year, the Charing Cross Symposium is launching the CX Live Case method. Thomas Zeller (Universitäts-Herzzentrum Freiburg – Bad Krozingen, Bad Krozingen, Germany), course director of the CX Live Peripheral Arterial Cases, will link the live case demonstrations from Bad Krozingen with topics to be discussed in the CX Main Programme – Peripheral Arterial Controversies at the Charing Cross Symposium 2015.
Starting with shorter and simpler lesions, Zeller and his team will aim to demonstrate the value of drug-coated balloons against plain old balloon angioplasty. Beyond this, longer and also calcified arterial stenoses will be tackled. The audience will see which stents are selected, and whether atherectomy pre-stent is thought to be beneficial. Zeller will show which stent devices can reach longer lesions and into the popliteal artery, and which require pre-treatment with adjunctive therapies. The value of drug-eluting stents will also be demonstrated, and the management of in-stent restenosis and its correction by mechanical means will be shown.
In this interview, he explains the value of live case presentations at conferences and the importance of relating the CX Live Peripheral Arterial Cases to the topics of the CX Main Programme – Peripheral Arterial Controversies, and encourages audience interaction in this session.
What are the benefits of including live case presentations in medical conferences?
Live case presentations—provided they are unbiased—support the transfer of clinical science into clinical practice. New technologies and treatment algorithms can be demonstrated (supplementing talks and roundtable discussions) and the potential limitations and advantages in daily routine can be highlighted. With live case presentations; conference audience gets a better and practical impression of how new technologies can be implemented in the interventionalist’s routine.
What are the benefits of having the CX Live Peripheral Arterial Cases relate to what is discussed in the CX Main Programme – Peripheral Arterial Controversies?
The attendee gets immediate insights into the clinical application and potential pitfalls of new interventional strategies, which have been discussed in the CX Main Peripheral Programme (The CX Main Programme – Peripheral Arterial Controversies will take place on 28 April 2015, a day before the CX Live Peripheral Arterial Cases). Every new technology imposes a learning curve which might become shortened if the attendee gets advice from experienced operators who have already gained experience in the application of interventional strategies or use of those new technologies.
The live cases for the Charing Cross Symposium have been selected based on the topic of a given session to enable the panel and audience to discuss these topics with the operators.
The CX Main Programme – Peripheral Arterial Controversies dedicates a session to the discussion of revascularisation strategies in the superficial femoral artery; which key controversies will you try to shed light on with the CX Live Peripheral Arterial Cases session in this field?
In the CX Peripheral Live Cases, the main issue of controversy to discuss is the potential role of drug-coated balloons and drug-eluting stents for the treatment of the superficial femoral artery. We will analyse whether (or not) these devices are worth the costs compared to standard treatment (plain old balloon angioplasty and bare metal stenting). Moreover, the role of spot stenting in a drug-coated balloon setting will be discussed and finally the potential role of vessel preparation prior to the use of drug-eluting technologies.
What techniques and technologies will be demonstrated at the CX Live Peripheral Arterial Cases session?
We will show interventions dealing with drug-coated balloons and provisional stenting, stenting of kink zones, vessel preparation with debulking devices, how to treat in-stent reocclusions, etc.
The CX Symposium advocates strong audience interaction; how will you encourage participants’ interaction in the CX Live Peripheral Arterial Cases session?
Audience interaction has to be pushed by the moderators and panellists. We as operators will be open to questions from the audience and we will also invite the audience to express their own experiences with the interventional techniques, which will be shown during the live case transmissions.
The CX Live Peripheral Arterial Cases session will take place at the Charing Cross Symposium on Wednesday 29 April – Grey Learning Centre, Olympia Grand, London, UK
Click here to see the CX Main Programme Sessions
Click here to see the CX Parallel Sessions
Click here to register
Intravascular imaging important to avoid rupture after blunt aortic injury

Benjamin Starnes (Seattle, USA) told the audience attending yesterday’s mini symposium on acute aortic transection that intravascular ultrasound (IVUS) was an important tool in the management of patients with blunt aortic injury undergoing thoracic endovascular aortic repair (TEVAR) because it helps to ensure accurate sizing of the endograft and prevent rupture. The session also reviewed the differences between image-based classifications of blunt aortic injury.
Starnes reported that, over the past decade, endovascular repair of patients with blunt traumatic aortic injury has become the “predominant approach to fixing these injuries”, but added that there were “unique challenges” to using the endovascular approach. He said: “One of challenges is the dynamic nature of the aorta. There are some interesting data from blood-letting studies in Yorkshire pigs that show significant decrease in aortic diameter accompanying induced haemorrhagic shock, with a dose-dependent effect.”
According to Starnes, aortic diameter is also known to increase after resuscitation and the area with the greatest change in size is the area that is most commonly injured in blunt trauma (ie. the isthmus and descending aorta). He added: “CT angiography is used for diagnosis of these injuries and axial slices from the initial scan are often used for planning and sizing of the repair. While using IVUS at the time of repair to better characterise the injury, we noticed a difference in the aortic diameter with systolic variation [compared with the diameter observed on the initial CT angiography]. This then begs the questions “Is initial CT angiography appropriate for sizing the endograft in these patients?” and “Is that endograft going to be undersized once that patient is fully resuscitated?”
Starnes and colleagues, therefore, conducted a retrospective chart review of patients with blunt aortic injury who underwent TEVAR at their level-one trauma centre to determine if there was a difference between the aortic diameter observed on diagnostic CT angiography and that observed on IVUS at the time of the repair. The inclusion criteria were initial admission or pre-admission CT angiography, IVUS at the time of repair, and a post-implant CT angiography. Of the 26 patients who were treated at the centre during the study period (July 2007–July 2011), three patients did not have post-implant CT angiography information, one patient was converted to surgery, and six patients did not receive IVUS—leaving 16 patients available for assessment.
There was a significant difference of 2.4mm between mean aortic diameter with initial CT angiography and mean aortic diameter with IVUS: 21.7mm vs. 24mm, respectively (p=0.004). Starnes noted: “When we look at post-implant CT angiography compared with initial CT angiography, there is again a highly significant difference of 3mm (p=0.0001). But, when we compared post-implant CT angiography with IVUS, there was no difference.” He added that when they reviewed theoretical graft diameters, there was a significant difference of 2.4mm (p=0.003) between the size of the graft that would be chosen based on the initial CT angiography and that based on IVUS at time of repair. There was also a significant difference in graft size between post-implant CT angiography and initial CT angiography (3mm; p=0.0002), but no difference in size between post-implant CT angiography and IVUS.
“I believe IVUS is a critical and important tool for the management of patients with blunt aortic injury,” Starnes concluded.
Ali Azizzadeh (Houston, USA) also presented data at the mini symposium, reviewing the long-term effects of intentional stent graft coverage of the left subclavian artery (in patients with blunt aortic injury undergoing TEVAR). He said that in a review of 82 patients undergoing TEVAR at his centre between September 2005 and July 2012, 50 received intentional stent graft coverage of their left subclavian artery. Azizzadeh reported: “Intentional coverage of the left subclavian artery during TEVAR for blunt aortic injury appears safe without compromising mental or physical health outcomes. Furthermore, left artery stent coverage does not increase the long-term risk of upper extremity symptoms or impairment of normal activities.”
Does intramural haematoma exist?
As well as presenting data for the role of IVUS in the management of patients with aortic, Starnes also reviewed the classification of the injury. He reported that he and his colleagues developed a new image-based classification system for these types of injury because they believed the current classification system, by the Society for Vascular Surgery (SVS), was “lacking”. Starnes explained: “The SVS system has four grades of injury—grade one, intimal tear; grade two, intramural haematoma; grade three, pseudoaneurysm; and grade four, rupture—but does not provide for any treatment recommendations because grades one to three are treated the same and we do not believe grade two exists. In a review of 140 aortic transections at our centre, we did not see a single case of intramural haematoma.”
Therefore, they developed a new classification system based on the presence or absence of an aortic external contour abnormality. Under this new system, intimal tear (intimal defect and/or thrombus of
However, Michael Dake (Stanford, USA) commented that there was a lack of consensus surrounding intramural haematoma as unlike Starnes and colleagues, Rabin and colleagues did recognise the existence of intramural haematoma and classified it as being a “grade one” injury (in contrast to the SVS classification). He added that Osgood and colleagues, in an another system, classed intramural haematoma as being “grade 1B” but he noted that they did not find any patients with that type of injury in their series. Dake reported, regardless of how it was classified, recent publications have suggested that: “Intramural haematoma without associated peri-aortic component, contour abnormality, or pseudoaneurysm may be conservatively managed with appropriate follow-up imaging.”
CX audience unconvinced about early intervention for uncomplicated type B dissections

The CX Great Debate saw Peter Taylor, London, UK, and Richard Gibbs, Imperial College, London, UK, persuaded 71% of the audience at the Charing Cross International Symposium yesterday to vote for their position against the motion “For uncomplicated type B dissections, early intervention is indicated”.
Their opponents in the debate, Christoph Nienaber, Rostock, Germany, and Jan Brunkwall, Köln, Germany, had the support of 29% of the audience. Audience discussion at the end of the session identified a need for a larger randomised trial with long-term follow-up that had clinically meaningful endpoints.
Nienaber and Brunkwall set out to persuade the audience that placing a stent graft early was important in order to heal the aorta. “Rupture, malperfusion, hypertension and down the line, aneurysm formation are some of the risks of type B dissection,” Brunkwall said.
Nienaber made the point that scaffolding was the only way to stabilise the progression of the dissection as data available so far showed that the disease is characterised by a downhill evolution over time. “If there is no scaffold, and the aorta is not remodelled, you are confronted with ongoing attrition rate in terms of cardiovascular death and progression of the disease. This is beneficial for even in so called stable or clinically silent patients,” he said. He made his views clear that no dissection was ever uncomplicated.
“Only pre-emptive stenting will ensure long-term remodelling and stability. Only remodelling stabilises the aorta and no drug that induces remodelling, only the likelihood of rupture, so supportive scaffolding should be offered to any type B dissection,” Nienaber said.
“What do we achieve with TEVAR in the setting of type B acute dissections? Fewer later interventions and lower mortality after five years,” Brunkwall said. The five-year long-term follow-up of the INSTEAD XL showed a statistically significant reduction in aorta-specific mortality and a statistically significant reduction in disease progression in favour of the combined TEVAR plus medical therapy arm.
Brunkwall also made the point that the ADSORB trial with false lumen thrombosis as an endpoint, had shown that patients receiving TEVAR have significantly more complete and partial thrombosis than the ones getting best medical therapy.
The ADSORB trial was a prospective randomised trial to compare TEVAR with best medical therapy in patients with acute uncomplicated type B aortic dissection. At the follow-up for one year, there was no death stroke or paraplegia in either group at 30 days and aortic remodelling at one year favoured the intervention but it did not reach statistical significance.
Taylor and Gibbs based their arguments around the fact that medical treatment is getting better. Briggs noted that a recent study (Fattori et al. J Am Coll Cardiol 2013;61:1661-78) had shown that survival at five years without intervention is 70–89%. They also highlighted the fact that TEVAR carries risks including retrograde dissection; stroke (3%); paraplegia (2.5%) and other complications. The team stated that all current endografts used in dissection are designed for use in aneurysms.
“There is no adequate evidence to recommend early intervention in all but a few patients with uncomplicated type B dissection. Only a small subgroup at high risk of aortic expansion will benefit from early intervention and these patients can be identified using techniques such as functional imaging,” Briggs said
Taylor also attacked the quality of evidence from randomised controlled trials that supported early intervention. “The ADSORB trial had only 61 patients in total. It was underpowered and stopped at one year and was therefore too short and small to answer questions about survival and efficacy. The INSTEAD trial had only 140 patients in total and underpowered for survival. In total, there have been only 201 dissection patients ever randomised,” he said.
Taylor made the point that drug therapy was getting better and that the available evidence showed that the majority of patients are alive with medical treatment; there is 80% survival at five years and that therefore, medical treatment was safe for the majority of patients with uncomplicated type B dissection. They do not need early intervention and there is an early mortality associated with TEVAR that cannot be ignored, he said.
A member of the audience noted that in order to make a clinical difference, all-cause mortality has to be the only endpoint at five years and the trial should be designed to show superiority. Martin Bjorck, Uppsala, Sweden, also commented on the difficulty faced in every day clinical practice. “There is a problem because we know from the data from the two randomised trials that it is rather safe to do TEVAR, but that there is a 3–5% risk of very serious neurological complications that cannot be discounted. We know from the long-term results of the INSTEAD trial that if you do not treat, you have many patients developing dilatations and needing treatment later on that is more complicated. We need a larger randomised trial with long-term follow-up.”
CX voting results
Earlier in the session, 65% of the CX audience had voted that registry data is now irrelevant and that it was time that randomised trial evidence for TEVAR dissection became available. Nearly 80% also believed that aortic intervention for acute dissection should only be performed in recognised vascular centres with cardiothoracic surgery on site.